Εμφάνιση αναρτήσεων με ετικέτα COVID-19. Εμφάνιση όλων των αναρτήσεων

Σάββατο 9 Ιανουαρίου 2021

TOCLIZUMAB FOR SEVERE COVID

 Treating critically ill COVID-19 patients with Roche's Actemra or Sanofi's Kevzara arthritis drugs significantly improves survival rates and reduces the amount of time patients need intensive care, study results showed on Thursday.

The findings, which have not yet been peer-reviewed, showed that the immunosuppressive drugs - Actemra, also known as tocilizumab, and Kevzara, also known as sarilumab - reduced death rates by 8.5 percentage points among patients hospitalised and severely ill with the pandemic disease.

That would mean that for every 12 patients treated with one of the two drugs, an extra life would be saved, said Anthony Gordon, an Imperial College London professor of anaesthesia and critical care who co-led the study.

The data will boost confidence that some existing drugs could be repurposed to help with the pandemic that has killed more than 1.87 million people and crushed global economies.

It also comes as countries struggle to contain two variants of the virus found in South Africa and Britain that are more transmissible and have driven a surge in infections.

Drug companies have been scouring their existing portfolios for possible therapies. So far the generic steroid dexamethasone and Gilead's antiviral drug remdesivir have been approved for treating patients with severe symptoms.

The United States has also authorised emergency use of some antibody drugs for non-hospitalised COVID-19 patients.

The data, from around 800 severely ill COVID-19 patients involved in an international study known as the REMAP-CAP trial showed that the two drugs reduced mortality rates from 35.8% in a control group to 27.3% among patients receiving either tocilizumab or sarilumab.

"That's a big change in survival," said Gordon. "They are both lifesaving drugs."

The results also showed that on average, patients treated with Actemra or Kevzara recovered more swiftly and were able to be discharged from intensive care units around seven to 10 days earlier than those who did not get these drugs, Gordon said.

"This ... could have immediate implications for the sickest patients with COVID-19," he added. "We're seeing the actual benefit in terms of survival and quicker recovery."

Until now, results for Actemra and Kevzara - both a type of drug known as IL-6 receptor antagonists - in treatment trials in patients with COVID-19 have been mixed.

Sanofi said in September that Kevzara - which it produces with partner Regeneron - failed to meet the main goals of a U.S. study testing it in critically ill COVID-19 patients.

In November, Roche said research showed Actemra helped the sickest COVID-19 patients, but it was unclear if it kept people alive or shortened how long they needed intensive care support such as mechanical ventilation, or both.

Gordon noted on Thursday that previous studies had found no clear benefit, but said those trials had included less severely ill patients and started treatment at different stages in the disease course.

"A crucial difference may be that in our study, critically ill patients were enrolled within 24 hours of starting organ support," he said. "This highlights a potential early window for treatment where the sickest patients may gain the most benefit from immune modulation treatment."

Τετάρτη 6 Ιανουαρίου 2021

COVID NEWS-FACE MASKS VACCINE DOSING


FDA Statement on Following the Authorized Dosing Schedules for COVID-19 Vaccines


Get Permission

On January 4, U.S. Food and Drug Administration (FDA) Commissioner Stephen M. Hahn, MD, and Director of the FDA’s Center for Biologics Evaluation and Research Peter Marks, MD, PhD, issued the following statement on FDA-authorized dosing schedules for each COVID-19 vaccine.

Photo credit: Getty

Two different mRNA vaccines have now shown remarkable effectiveness of about 95% in preventing COVID-19 infection in adults. As the first round of vaccine recipients become eligible to receive their second dose, we want to remind the public about the importance of receiving COVID-19 vaccines according to how they’ve been authorized by the FDA in order to safely receive the level of protection observed in the large, randomized trials supporting their effectiveness.

We have been following the discussions and news reports about reducing the number of doses, extending the length of time between doses, changing the dose (half-dose), or mixing and matching vaccines in order to immunize more people against COVID-19. These are all reasonable questions to consider and evaluate in clinical trials. However, at this time, suggesting changes to the FDA-authorized dosing or schedules of these vaccines is premature and not rooted solidly in the available evidence. Without appropriate data supporting such changes in vaccine administration, we run a significant risk of placing public health at risk, undermining the historic vaccination efforts to protect the population from COVID-19.

The available data continue to support the use of two specified doses of each authorized vaccine at specified intervals. For the Pfizer-BioNTech COVID-19 vaccine, the interval is 21 days between the first and second dose. For the Moderna COVID-19 vaccine, the interval is 28 days between the first and second dose.

What we have seen is that the data in the firms’ submissions regarding the first dose is commonly being misinterpreted. In the phase III trials, 98% of participants in the Pfizer-BioNTech trial and 92% of participants in the Moderna trial received two doses of the vaccine at either a 3- or 4-week interval, respectively. Those participants who did not receive two vaccine doses at either a 3-or 4-week interval were generally only followed for a short period of time, such that we cannot conclude anything definitive about the depth or duration of protection after a single dose of vaccine from the single-dose percentages reported by the companies.

Using a single-dose regimen and/or administering less than the dose studied in the clinical trials without understanding the nature of the depth and duration of protection that it provides is concerning, as there is some indication that the depth of the immune response is associated with the duration of protection provided. If people do not truly know how protective a vaccine is, there is the potential for harm because they may assume that they are fully protected when they are not, and accordingly, alter their behavior to take unnecessary risks.

We know that some of these discussions about changing the dosing schedule or dose are based on a belief that changing the dose or dosing schedule can help get more vaccine to the public faster. However, making such changes that are not supported by adequate scientific evidence may ultimately be counterproductive to public health.

We have committed time and time again to make decisions based on data and science. Until vaccine manufacturers have data and science supporting a change, we continue to strongly recommend that health-care providers follow the FDA-authorized dosing schedule for each COVID-19 vaccine. The content in this post has not been reviewed by the American Society of Clinical Oncology, Inc. (ASCO®) and does not necessarily reflect the ideas and opinions of ASCO®.


(Reuters Health) - Two new literature reviews suggest face masks provide some protection to the wearer and when universally worn by the general public they substantially reduce the spread of the new coronavirus. The reviews, published in Annals of Internal Medicine, look specifically at the effect of masking on COVID-19 transmission. One report analyzed the impact of masking by the general public on the spread of the virus. Researchers reviewed over 100 research articles and concluded that masking could substantially reduce the spread of viruses, including SARS-CoV-2, without risks to the wearer. "Our review clearly shows that masks and face coverings worn by members of the public are highly effective in reducing the spread of SARS-CoV-2," said study leader Dr. Thomas Czypionka, head of the Health Economics and Health Policy Unit at the Institute for Advanced Studies in Vienna, Austria and visiting senior research fellow at the London School of Economics and Political Science. "A growing body of evidence suggests that the virus is transmitted through drops in close contact situations and through aerosols, small particles hovering in the air for extended periods of time that accumulate especially in closed and crowded spaces," Dr. Czypionka said in an email. "Such situations should be avoided of course, but if you can't - for example, on public transport, in shops etc. - masks and face coverings can substantially reduce the risk of infection, mainly by source control, that is, by trapping the particles exhaled. There is also laboratory evidence that they may protect the wearer as well. Therefore, masks can literally save lives, and in a situation like this, with community spread, they should be widely used." There are many misconceptions about masks, Dr. Czypionka said. "One is that they lead to physiological changes like elevated carbon dioxide levels or decreased oxygen levels in the blood," he added. "Masks and face coverings may cause discomfort for some people, but we found no empirical evidence for masks to cause harm." The second report -- an update to a "living review" of data on mask use by the general public and by health care workers -- focused mainly on three studies: one study of masking and the prevention of SARS-CoV-2 in a community setting (the DANMASK trial) and two studies of mask use in healthcare settings. The DANMASK open label trial, which included 6,024 community dwelling adults in Denmark, found that the incidence of SARSCoV-2 infection among participants was 2%. Surgical mask use as compared to no mask use was associated with a small reduction in risk for infection, but the finding was not statistically significant, the researchers noted. "The study suggests that masks may have small benefits in reducing the risk of infection in the wearer," said the report's lead author, Dr. Roger Chou, a professor in the School of Medicine at the Oregon Health and Sciences University. Unfortunately, Denmark is a place where it would be harder to show benefits because the infection rate there is low and people have been good about following guidelines, such as social distancing and handwashing, Dr. Chou said. "One important reason to wear masks is to prevent those who don't realize they are infected or have mild symptoms from infecting others," Dr. Chou said. "But this study wasn't designed to evaluate that." Of the two other studies, one, which included 16,397 health care workers and first responders, found that use of an N95 or surgical mask all of the time versus not all of the time was associated with a decreased risk for infection. The second study, which included 20,614 asymptomatic health care workers, found that the risk for infection was reduced with any mask use versus no mask use. The update of the living rapid review is important, said Juan Jesus Carrero, a professor of epidemiology in the department of medical epidemiology and statistics at the Karolinska Institute in Stockholm. "In interpreting the results of the DANMASK study, it is essential to remember that it was not a study of source control, and therefore doesn't tell us about the ability of community mask wearing to reduce overall transmission in the pandemic," Carrero said in an email. The new information included in Dr. Chou's study was welcomed by Dr. Catherine Clase, an associate professor in the department of medicine at McMaster University and a member of the Centre of Excellence in Protective Equipment and Materials. "The two additional observational studies on mask wearing are consistent with the expected degree of protection based on the authors' previous work and the meta-analysis on the effects of masks in the transmission of non-COVID coronaviruses," Dr. Clase said in an email. Face Masks Protect Wearers, Others From COVID: Studies 1/6/2021 https://www.medscape.com/viewarticle/943412_print https://www.medscape.com/viewarticle/943412_print 2/2 The Czypionka article highlighted the importance of masking to prevent the spread of COVID-19, Dr. Clase said. "I agree with their assessment that masks can play an important role in reducing the spread of particles of all sizes," she added. Calling the Czypionka article "outstanding," Carrero applauded the authors for pulling together "a network of evidence on the diverse questions which have surrounded mask use since the beginning of the pandemic. As they summarize, universal community masking has been associated with fewer new cases and lower mortality in every study to examine this question." SOURCE: https://bit.ly/2L8l6h3 and https://bit.ly/3n3olDD Annals of Internal Medicine, online December 29, 2020. Reuters Health Information © 2020 Cite this: Face Masks Protect Wearers, Others From COVID: Studies - Medscape - Dec 30, 2020


Δευτέρα 4 Ιανουαρίου 2021

COVID NEWS


An international team of clinicians and researchers have described the pathology of the novel coronavirus, or COVID-19, for the first time. Their findings were published by Tian et al in the Journal of Thoracic Oncology.

The article’s senior author, Shu-Yuan Xiao, MD, from the University of Chicago Medicine in Chicago, teamed up with a small group of clinicians from the Zhongnan Hospital of Wuhan University, in Wuhan, China.

Photo credit: Getty

The article describes two patients who recently underwent lung lobectomies for adenocarcinoma and were retrospectively found to have had COVID-19 at the time of surgery. Pathologic examinations revealed that, apart from the tumors, the lungs of both patients exhibited edema, proteinaceous exudate, focal reactive hyperplasia of pneumocytes with patchy inflammatory cellular infiltration, and multinucleated giant cells. Fibroblastic plugs were noted in airspaces.

“This is the first study to describe the pathology of disease caused by...COVID-19 pneumonia, since no autopsy or biopsies had been performed thus far. This would be the only description of early-phase pathology of the disease due to this rare coincidence...Since both patients did not exhibit symptoms of pneumonia at the time of surgery, these changes likely represent an early-phase of the lung pathology of COVID-19 pneumonia," Dr. Xiao said.

Two Cases

The first case was an 84-year-old female patient who was admitted for treatment evaluation of a tumor measuring 1.5 cm in the right middle lobe of the lung. The tumor was discovered on chest computed tomography scan at an outside hospital. She had a past medical history of hypertension for 30 years, as well as type 2 diabetes. Despite comprehensive treatment, assisted oxygenation, and other supportive care, the patient’s condition deteriorated, and she died. Subsequent clinical information confirmed that she was exposed to another patient in the same room who was subsequently found to be infected with the 2019 novel coronavirus.

The second case was a 73-year-old male patient who presented for elective surgery for lung cancer, which presented as a small mass in the right lower lobe of the lung. He had a past medical history of hypertension for 20 years, which had been adequately managed. Nine days after lung surgery, he developed a fever with dry cough, chest tightness, and muscle pain. A nucleic acid test for COVID-19 came back as positive. He gradually recovered and was discharged after 20 days of treatment in the infectious disease unit.

Common Scenario

According to the study, these two incidences also typify a common scenario during the earlier phase of the COVID-19 outbreak, during which a significant number of health-care providers became infected in hospitals in Wuhan, and patients in the same hospital room were cross-infected as they were exposed to unknown infectious sources. The presence of early lung lesions days before the patients developed symptoms corresponds to the long incubation period (usually 3 to 14 days) of COVID-19.

The long incubation period made it difficult to prevent transmission during the early days of this outbreak, as many health-care workers in Wuhan became infected when they were seeing patients without sufficient protection, according to Dr. Xiao. As of today, more than 15 doctors in Wuhan have died of COVID-19.

“We believe it is imperative to report the findings of routine histopathology for better understanding of the mechanism by which [COVID-19] causes lung injury in the unfortunate tens and thousands of patients in Wuhan and worldwide,” said Dr. Xiao.

Further studies by Dr. Xiao’s team and collaborators on COVID-19 pathology through postmortem biopsies are ongoing, which should provide data on the late changes of this disease.


 Editor's note: Find the latest COVID-19 news and guidance in Medscape's Coronavirus Resource Center. The CDC has issued updated guidance for people with underlying medical conditions who are considering getting the coronavirus vaccine. "Adults of any age with certain underlying medical conditions are at increased risk for severe illness from the virus that causes COVID-19," the CDC said in the guidance posted on Saturday. "mRNA COVID-19 vaccines may be administered to people with underlying medical conditions provided they have not had a severe allergic reaction to any of the ingredients in the vaccine." Both the Pfizer and Moderna vaccines use mRNA, or messenger RNA. The CDC guidance had specific information for people with HIV, weakened immune systems, and autoimmune conditions such as Guillain-Barre syndrome and Bell's palsy who are thinking of getting the vaccine. People with HIV and weakened immune systems "may receive a COVID-19 vaccine. However, they should be aware of the limited safety data," the CDC said. There's no information available yet about the safety of the vaccines for people with weakened immune systems, the CDC said. People with HIV were included in clinical trials, but "safety data specific to this group are not yet available at this time," the CDC said. Cases of Bell's palsy, a temporary facial paralysis, were reported in people receiving the Pfizer and Moderna vaccines in clinical trials, the FDA said Dec. 17. But the new CDC guidance says the FDA "does not consider these to be above the rate expected in the general population. They have not concluded these cases were caused by vaccination. Therefore, persons who have previously had Bell's palsy may receive an mRNA COVID-19 vaccine." Researchers have determined the vaccines are safe for people with GBS, a rare autoimmune disorder in which the body's immune system attacks nerves just as they leave the spinal cord, the CDC said. "To date, no cases of Guillain-Barre syndrome (GBS) have been reported following vaccination among participants in the mRNA COVID-19 vaccine clinical trials," the CDC guidance says. "With few exceptions, the independent Advisory Committee on Immunization Practices (ACIP) general best practice guidelines for immunization do not include a history of GBS as a precaution to vaccination with other vaccines." For months, the CDC and other health authorities have said that people with certain medical conditions are at an increased risk of developing severe cases of COVID-19. Sources: CDC: "COVID-19 Vaccination Considerations for Persons with Underlying Medical Conditions"

Now that COVID-19 vaccines are being distributed, the American Association for Cancer Research (AACR) has called for people with cancer to be considered as a high priority group. "The available evidence supports the conclusion that patients with cancer, in particular with hematological malignancies, should be considered among the high-risk groups for priority COVID-19 vaccination," says the AACR's COVID-19 and Cancer Task Force. A review of literature suggests that COVID-19 fatality rates for patients with cancer were double that of individuals without cancer, the team notes. The higher mortality rates still trended upward, even after adjusting for confounders including age, sex, and comorbidities, indicating that there is a greater risk for severe disease and COVID-19 related mortality. The new AACR position paper was published online December 19 in Cancer Discovery. "We conclude that patients with an active cancer should be considered for priority access to COVID-19 vaccination, along other particularly vulnerable populations with risk factors for adverse outcomes with COVID-19," the team writes. However, the authors note that "it is unclear whether this recommendation should be applicable to patients with a past diagnosis of cancer, as cancer survivors can be considered having the same risk as other persons with matched age and other risk factors. "Given that there are nearly 17 million people living with a history of cancer in the United States alone, it is critical to understand whether these individuals are at a higher risk to contract SARS-COV-2 and to experience severe outcomes from COVID-19," they add. Allocation of Initial Doses There has already been much discussion on the allocation of the initial doses of COVID-19 vaccines that have become available in the US. The Advisory Committee on Immunization Practices (ACIP) of the Centers for Disease Control and Prevention (CDC) recommended that the first wave of vaccinations, described as Phase 1a, should be administered to US healthcare workers (about 21 million people) and residents of long-term care facilities (about 3 million). The next priority group, Phase 1b, should consist of front-line essential workers, a group of about 30 million, and adults aged 75 years or older, a group of about 21 million. When overlap between the groups is taken into account, Phase 1b covers about 49 million people, according to the CDC. Finally, Phase 1c, the third priority group, would include adults aged 65-74 years (a group of about 32 million), adults aged 16-64 years with high-risk medical conditions (a group of about 110 million), and essential workers who did not qualify for inclusion in Phase 1b (a group of about 57 million). With the overlap, Phase 1c would cover about 129 million people. "Cancer is one of the categories of individuals at high risk," said Antoni Ribas, MD, PhD, AACR president and chair of the AACR COVID-19 and Cancer Task Force. "At the ACIP vote on December 20, the priority access was assigned to Phase 1c, but this results in a potential significant delay in vaccination for the particularly vulnerable population of patients with cancer at this time of highest risk, with the winter worsening of the COVID-19 pandemic." "Any delay in vaccine access will result in loss of life that could be prevented with earlier access to vaccination," Ribas told Medscape Medical News. He noted that the task force agrees that people whose work is essential to run society should receive priority vaccination, but consideration should be given to first vaccinating patients with cancer who are at increased risk of dying if they get COVID-19. "This would include the 2 or 3 million people in the US who currently are receiving treatments for cancer, in particular if they have blood cancers or lung cancer, as they are at a particularly higher risk of dying based on the studies we reviewed," he said. Patients With Cancer a 'High Priority' for COVID-19 Vaccine 1/4/2021 https://www.medscape.com/viewarticle/943308_print https://www.medscape.com/viewarticle/943308_print 2/3 "Moreover, a subset of cancer patients appears to have prolonged viral shedding, placing their healthcare providers and caregivers at higher risk." The best scenario, Ribas emphasized, "would be that with two approved COVID-19 vaccines there is enough stock in the next few weeks to vaccinate all individuals assigned to Phase 1b and 1c." Questions Remain Approached for independent comment, Cardinale Smith, MD, PhD, chief quality officer for cancer services for the Mount Sinai Health System in New York City, agreed with the AACR task force. "I share that they should be high priority," she said, "But we don't know that the efficacy will the same." Smith noted that the impact of cancer therapy on patient immune systems is more related to the type of treatment they're receiving, and B and T cell responses. "But regardless, they should be getting the vaccine, and we just need to follow the guidelines," she said. The AACR task force notes that information thus far is quite limited as to the effects of COVID-19 vaccination in patients with cancer. In the Pfizer-BioNTech BNT162b2 COVID vaccine trial, of 43,540 participants, only 3.7% were reported to have cancer. "It is clear that we need more data and specific studies in patients with cancer, but this should not delay access to priority vaccination," said Ribas. "There is considerable experience with other vaccines, such as the yearly flu vaccine, in cancer patients with very good safety records." Other large COVID-19 vaccine trials will provide further follow-up information on the effectiveness of the vaccines in patients receiving different cancer treatments, they write, but for now, there is "currently not enough data to evaluate the interactions between active oncologic therapy with the ability to induce protective immunity" to COVID-19 with vaccination. Ribas pointed out that studies of natural immune response to COVID-19 have documented that patients with hematologic malignancies have a suboptimal ability to mount an immune response to the virus. This results in these patients having a "remarkably" high risk of fatality compared with other patient populations with COVID-19 infection. "The fact that the antibody and T-cell responses to the COVID-19 vaccines are higher than in many individuals with natural COVID-19 infection provides an even stronger rationale to offer vaccination to persons with lower immune responses to the virus," he said. "Although ongoing studies will provide more information about how to best protect cancer patients with vaccines, at present, there is no evidence that the vaccine should be delayed in cancer patients. "Of course, patients with cancer should consult with their healthcare providers about their potential risks and benefits to decide whether getting vaccinated is right for them," he added. In a recent interview with Medscape Medical News, Nora Disis, MD, a medical oncologist and director of both the Institute of Translational Health Sciences and the Cancer Vaccine Institute, University of Washington, Seattle, also discussed vaccinating cancer patients. She pointed out that even though there are data suggesting that cancer patients are at higher risk, "they are a bit murky, in part because cancer patients are a heterogeneous group." "For example, there are data suggesting that lung and blood cancer patients fare worse," said Disis, who is also editor-in-chief of JAMA Oncology. "There is also a suggestion that, like in the general population, COVID risk in cancer patients remains driven by comorbidities." She also pointed out the likelihood that individualized risk factors including the type of cancer therapy, site of disease, and comorbidities "will shape individual choices about vaccination among cancer patients." It is also reasonable to expect that patients with cancer will respond to the vaccines, even though historically some believed that they would be unable to mount an immune response. "Data on other viral vaccines have shown otherwise," said Disis. "For example, there has been a long history of studies of flu vaccination in cancer patients, and in general, those vaccines confer protection." Several of the authors of the AACR position paper, including Ribas, report relationships with industry as detailed in the paper.


Editor's note: Find the latest COVID-19 news and guidance in Medscape's Coronavirus Resource Center. Anthony Fauci, MD, says the coronavirus pandemic may get worse in coming months, including a post-holiday surge in cases. In an interview on CNN, Fauci was asked if he thought "the worst was yet to come." He said, "I do." "We very well might see a post-seasonal ― in the sense of Christmas, New Year's ― surge, and, as I have described it, as a surge upon a surge," said Fauci, the director of the National Institute of Allergy and Infectious Diseases. Fauci said holiday travel could cause a spike in cases. Besides exposing themselves at airports, travelers usually mix households when they arrive at their destinations, he said. Even though health authorities urge people not to travel, "it’s going to happen," Fauci said. "We are really at a very critical point. ... So I share the concern of President-elect (Joe) Biden that as we get into the next few weeks, it might actually get worse," Fauci said. Biden recently said that the "darkest days" in the coronavirus pandemic are ahead and urged Americans to prepare themselves for a difficult struggle. Fauci has agreed to serve as Biden’s top health adviser. December has already been the hardest month for the COVID-19 pandemic in the United States. More than 65,000 people have died of coronavirus-related reasons so far this month, compared to only about 37,000 in November, according to the Covid Tracking Project. Hospitalizations are up, with more than 100,000 people in the hospital per day since Dec. 2. Overall, there have been more than 19 million confirmed cases in the United States and more than 333,000 COVID-related deaths ― the most of any nation in the world. COVID-19 vaccinations should bring the pandemic under control, but it will take many months for the United States to develop herd immunity, Fauci said. Health care workers and residents of long-term care facilities are the top priority groups receiving the vaccine. "I hope that by the time we get to the fall we will reach that critical percentage of people that we can really start thinking about a return to some form of normality," Fauci said. Fauci, who just turned 80, got a COVID-19 vaccination recently. He said he had no side effects besides arm soreness for about 


Σάββατο 26 Δεκεμβρίου 2020

INCREASED LEVEL OF ANTICOAGULATION NOT USEFUK IN COVID

 Parts of three linked studies investigating increased levels of anticoagulation in hospitalized COVID-19 patients have been "paused" because of futility and safety concerns, a statement from the US National Heart, Lung, and Blood Institute (NHLBI) confirms.

The trials involved are the RE;MAP-CAP, ACTIV-4, and ATTACC studies.

All three trials have paused enrollment of critically ill COVID-19 patients requiring intensive care unit support for whom therapeutic doses of anticoagulation drugs did not reduce the need for organ support, the NHLBI statement notes.

The statement also says that a potential for harm in this subgroup could not be excluded, noting that increased bleeding is a known complication of full-dose anticoagulation. The trials are working urgently to undertake additional analyses, which will be made available as soon as possible.   

The three clinical trial platforms are working together to test the effects of full therapeutic doses of anticoagulants vs lower prophylactic doses in COVID-19 patients.

Informed by the deliberations of the data safety monitoring boards of these trials, all of the trial sites have paused enrollment of the most critically ill hospitalized patients with COVID-19. 

Enrollment continues in the trials for moderately ill hospitalized COVID-19 patients, the statement notes.  

"Whether the use of full-dose compared to low-dose anticoagulants leads to better outcomes in hospitalized patients with less COVID-19 severe disease remains a very important question," the NHLBI statement says.

Patients who require full dose anticoagulants for another medical indication are not included in these trials.

The statement explains that COVID-19 is associated with significant inflammation and clinical and pathologic evidence of widespread blood clots. These trials were launched because clinicians have observed that many patients ill with COVID-19, including those who have died from the disease, formed blood clots throughout their bodies, even in their smallest blood vessels. This unusual clotting can cause multiple health complications, including lung failure, myocardial infarction, and stroke. 

The three trials are the result of a collaboration between major international partners. The trials include: the Randomized, Embedded, Multi-factorial Adaptive Platform Trial for Community-Acquired Pneumonia (REMAP-CAP) Therapeutic Anticoagulation; Accelerating COVID-19 Therapeutic Interventions and Vaccines-4 (ACTIV-4) Antithrombotics Inpatient; and Antithrombotic Therapy to Ameliorate Complications of COVID-19 (ATTACC).

The trials, which span four continents, have the common goal of assessing the benefit of full doses of anticoagulants to treat moderately ill or critically ill adults hospitalized for COVID-19, compared with a lower dose often used to prevent blood clots in hospitalized patients.

In the United States, the ACTIV-4 trial is being led by a collaborative effort involving a number of universities, including the University of Pittsburgh and New York University.  

The trials are supported by multiple international funding organizations including the National Institutes of Health, Canadian Institutes of Health Research, the National Institute for Health Research (UK), the National Health and Medical Research Council (Australia), and the PREPARE and RECOVER consortia (European Union).

Risk-Benefit Ratio 'Not Favorable'

Judith Hochman, MD, director of the Clinical Cardiovascular Research Center at NYU Langone, who is principal investigator of the ACTIV-4 trial, explained to Medscape Medical News that all three trials are looking at the same question — whether full-dose therapeutic anticoagulation is superior to low-dose prophylactic anticoagulation with heparin or low molecular weight heparin in patients hospitalized with COVID-19.

The three trials started off slightly differently: REMAP began with only ICU patients but has broadened to include non-ICU patients as well, ATTACC started off with only non-ICU patients but has broadened to include ICU patients as well, and ACTIV-4 enrolled both ICU and non-ICU patients from the beginning.

The NHLBI is funding ACTIV-4, but the three trials are harmonizing the collection and review of data so they have greater power to show a result. "The vast majority of COVID trials are underpowered to come to any conclusions, so it is important to collaborate in this way," Hochman noted.

Elaborating on the reasons for pausing enrolment in the ICU cohort, she said, "We know full dose anticoagulation increases the risk of bleeding — that would be expected. But what we didn't know was whether it would have a greater efficacy compared to low-prophylactic doses in reducing critical illness. The primary endpoint of these trials in this ICU group was the number of organ support-free days — the number of days patients do not require vasopressor support, mechanical ventilation or high flow oxygen. Results so far show that the chance of seeing a difference in this outcome is very small if we continue," she said.    

"Given that the trial is unlikely to show a benefit and we know these full therapeutic doses of anticoagulation cause an increased bleeding risk, then there will not be a favorable risk-benefit."

The trial also has a key secondary endpoint of thrombotic events but that has not been analyzed and is not part of the current decision.

All three trials are continuing in the non-ICU patient group. These non-ICU patients make up 80% of the ACTIV-4 trial, more in the ATTACC trial, and less in the REMAP trial, Hochman reported. 

"It is very important to stress that these results do not apply to patients already on full dose anticoagulants for an approved indication," she cautioned. "We already know these patients with an approved indication for full dose anticoagulation have a positive risk benefit ratio, and they should not be concerned about the current findings. These trials are trying to prevent clots in critically ill patients who do not have an approved indication for full dose anticoagulation."

Asked how she recommends clinicians now treat these critically ill COVID patients in the ICU in terms of anticoagulation, Hochman said they have to use their clinical judgement. "Prophylactic doses of heparin/low molecular weight heparin are still indicated," she said. "Some centers are trying a slightly higher prophylactic dose but we don't have data on that yet."

Speculating on why the full dose anticoagulation did not show benefit, she suggested it might be too late in the course of the disease to make any difference. "What we've observed at autopsy is thrombi in the microcirculation as well as the large vessels. It may be too late to treat all those thrombi," she said. "We are still hopeful that higher doses of anticoagulation may show benefit earlier in the course of the disease."

The ACTIV-4 trial is actually made up of three different studies of anticoagulation in COVID-19 patients. ACTIV-4a is this study in hospitalized patients randomized to full-dose versus prophylactic-dose anticoagulation with heparin/LMW heparin.

The ACTIV-4b study is being conducted in nonhospitalized COVID patients looking at outpatient use of antithrombotic medication (aspirin or apixaban), and ACTIV-4c includes COVID-19 patients after they have been discharged from hospital and is testing low dose apixaban or placebo.

"The current announcement has no effect on ACTIV-4b or ACTIV-4c," Hochman noted.

Many Questions Remain

Commenting for Medscape Medical News, Gregg Stone, MD, Mount Sinai Heart Health System, New York, explained that autopsies in patients who have died of COVID-19 have shown widespread arterial and venous thrombosis, often not clinically evident, raising the hypothesis that anticoagulation might benefit such patients.

"Several questions arise," Stone said, including 1) whether any prophylactic anticoagulation is better than none; 2) whether full-dose anticoagulation is better than prophylactic-dose anticoagulation; 3) whether a new oral anticoagulant is more or less safe and/or efficacious than a heparin formulation; 4) whether anticoagulation is more likely to have a favorable safety and effectiveness endpoint in the early or late stages of the disease, he said.

"ACTIV-4 is addressing issues 2 and 4, but not issues 1 and 3," Stone said. "The [Data and Safety Monitoring Board (DSMB)] has now recommended pausing enrolment of those patients ill enough to be admitted to an ICU, but not earlier, suggesting that once the disease has progressed to a severe stage, full-dose anticoagulation is not beneficial (and may be harmful). Perhaps this is not a surprising finding."

But he says there is still a great deal that is not known. "Questions remaining include: What are the event rates that led to this pause? How ill were these patients? Were most intubated already with [acute respiratory distress syndrome] or was there similar lack of efficacy and possible harm in those not yet intubated, and/or with lesser radiographic abnormalities? What were the bleeding complications and the profile of the patients in whom bleeding occurred? And more."

Stone is part of a Mount Sinai group conducting the Freedom COVID-19 Anticoagulation trial in which 3600 hospitalized but less critically ill patients who are not intubated are randomized 1:1:1 to prophylactic-dose enoxaparin, full-dose enoxaparin, or apixaban.

"Given the different enrolment criteria and the fact that ACTIV-4 is continuing enrolment into the less severe strata, I don't anticipate major changes to our trial," he commented.

Similarly, other ongoing trials investigating different regimens of anticoagulation in COVID-19 patients will need to consider whether their studies need modification based on enrolment criteria and DSMB guidance, he said.

As to advice for practitioners, Stone recommends that they offer their patients participation in one of the ongoing randomized trials so these questions can be expeditiously answered. For those not within a randomized trial, because COVID-19 patients are at increased risk for bleeding, he recommends prophylactic-dose (and not full-dose) anticoagulation for those not at excessive risk for and without a definite indication for full-dose anticoagulation.

For more from theheart.org | Medscape Cardiology, follow us on Twitter and Facebook.

Παρασκευή 25 Δεκεμβρίου 2020

COVID VACCINE NEWS

 Phase 3 interim trial results from the Oxford/AstraZeneca vaccine have just been published in The Lancet. Previously, interim results were issued in a press release.

In today's paper, for participants who received two standard doses, vaccine efficacy was 62.1%.

In participants who received a low dose followed by a standard dose, efficacy was 90.0%.

This was described as "intriguingly high compared with the other findings in the study. Although there is a possibility that chance might play a part in such divergent results."

Professor Andrew Pollard, director of the Oxford Vaccine Group, Department of Paediatrics, University of Oxford, told a news briefing hosted by the Science Media Centre that the half dose, full dose approach that gave the best results wasn't planned. He dismissed concerns about the age of participants in that group saying the result "doesn't appear to be an age phenomenon".

Overall vaccine efficacy across both groups was 70.4%.

Regulators and UK vaccination advisers would have to assess which regimen might be selected for approval, Prof Pollard said.

The vaccine was found to be safe, the authors said, with only three out of 23,745 participants over a median of 3.4 months experiencing serious adverse events that were possibly related to a vaccine; one in the vaccine arm, one in the control arm, and one in a participant who remains masked to group allocation. All participants have recovered or are recovering, and remain in the trial.

The paper said: "A case of transverse myelitis was reported 14 days after ChAdOx1 nCoV-19 booster vaccination as being possibly related to vaccination, with the independent neurological committee considering the most likely diagnosis to be of an idiopathic, short segment, spinal cord demyelination."

Prof Pollard said: "I think today is an important landmark for us because the data package that is in this paper is being put forward to regulators to consider and to scrutinise so there's these two different aspects of scrutiny, there's the scientific peer review for publication, and also the regulatory processes which I'm sure we'll hear more about in the weeks ahead."

Professor Sarah Gilbert, Jenner Institute, Nuffield Department of Medicine, University of Oxford, said: "This is a really good day in the UK. This is probably the best day we've had in 2020. Not only today are we seeing the first rollout of NHS vaccinations against COVID-19, from our side we're able to present to you our data in a full peer reviewed publication."

Reaction

In a linked comment, Dr Maria Deloria Knoll and Dr Chizoba Wonodi, Johns Hopkins Bloomberg School of Public Health, USA, who were not involved in the study, said: "Despite the outstanding questions and challenges in delivering these vaccines, it is hard not to be excited about these findings and now the existence of three safe and efficacious COVID-19 vaccines, with 57 more in clinical trials."

Professor Stephen Evans, professor of pharmacoepidemiology, London School of Hygiene & Tropical Medicine, commented: "These results reflect the headlines given in previous press releases, but with both a fuller explanation of what was done and more detail around the uncertainty in the estimates of efficacy.

"The unfortunate [half dose] measurement technique problem that occurred with some doses produced in Italy is going to be seen by some as raising questions about this trial. It is clear however, that national and international regulators were fully apprised of what had happened and a plan for analysis was determined prior to knowledge of the results." 

This article originally appeared on Medscape UK, part of the Medscape Professional Network.

For more news, follow Medscape on Facebook, Twitter, Instagram, and YouTube.


Coronavirus vaccines have become a reality, as they are now being approved and authorized for use in a growing number of countries including the United States. The U.S. Food and Drug Administration has just issued emergency authorization for the use of the COVID-19 vaccine produced by Pfizer and BioNTech. Close behind is the vaccine developed by Moderna, which has also applied to the FDA for emergency authorization.

The efficacy of a two-dose administration of the vaccine has been pegged at 95.0%, and the FDA has said that the 95% credible interval for the vaccine efficacy was 90.3%-97.6%. But as with many initial clinical trials, whether for drugs or vaccines, not all populations were represented in the trial cohort, including individuals who are immunocompromised. At the current time, it is largely unknown how safe or effective the vaccine may be in this large population, many of whom are at high risk for serious COVID-19 complications.

At a special session held during the recent annual meeting of the American Society of Hematology, Anthony Fauci, MD, the nation's leading infectious disease expert, said that individuals with compromised immune systems, whether because of chemotherapy or a bone marrow transplant, should plan to be vaccinated when the opportunity arises.

In response to a question from ASH President Stephanie J. Lee, MD, of the Fred Hutchinson Cancer Center, Seattle, Fauci emphasized that, despite being excluded from clinical trials, this population should get vaccinated. "I think we should recommend that they get vaccinated," he said. "I mean, it is clear that, if you are on immunosuppressive agents, history tells us that you're not going to have as robust a response as if you had an intact immune system that was not being compromised. But some degree of immunity is better than no degree of immunity."

That does seem to be the consensus among experts who spoke in interviews: that as long as these are not live attenuated vaccines, they hold no specific risk to an immunocompromised patient, other than any factors specific to the individual that could be a contraindication.

"Patients, family members, friends, and work contacts should be encouraged to receive the vaccine," said William Stohl, MD, PhD, chief of the division of rheumatology at the University of Southern California, Los Angeles. "Clinicians should advise patients to obtain the vaccine sooner rather than later."

Kevin C. Wang, MD, PhD, of the department of dermatology at Stanford (Calif.) University, agreed. "I am 100% with Fauci. Everyone should get the vaccine, even if it may not be as effective," he said. "I would treat it exactly like the flu vaccines that we recommend folks get every year."

Wang noted that he couldn't think of any contraindications unless the immunosuppressed patients have a history of severe allergic reactions to prior vaccinations. "But I would even say patients with history of cancer, upon recommendation of their oncologists, are likely to be suitable candidates for the vaccine," he added. "I would say clinicians should approach counseling the same way they counsel patients for the flu vaccine, and as far as I know, there are no concerns for systemic drugs commonly used in dermatology patients."

However, guidance has not yet been issued from either the FDA or the Centers for Disease Control and Prevention regarding the use of the vaccine in immunocompromised individuals. Given the lack of data, the FDA has said that "it will be something that providers will need to consider on an individual basis," and that individuals should consult with physicians to weigh the potential benefits and potential risks.

The CDC's Advisory Committee on Immunization Practices has said that clinicians need more guidance on whether to use the vaccine in pregnant or breastfeeding women, the immunocompromised, or those who have a history of allergies. The CDC itself has not yet released its formal guidance on vaccine use.

COVID-19 Vaccines

Vaccines typically require years of research and testing before reaching the clinic, but this year researchers embarked on a global effort to develop safe and effective coronavirus vaccines in record time. Both the Pfizer/BioNTech and Moderna vaccines have only a few months of phase 3 clinical trial data, so much remains unknown about them, including their duration of effect and any long-term safety signals. In addition to excluding immunocompromised individuals, the clinical trials did not include children or pregnant women, so data are lacking for several population subgroups.

But these will not be the only vaccines available, as the pipeline is already becoming crowded. U.S. clinical trial data from a vaccine jointly being developed by Oxford-AstraZeneca, could potentially be ready, along with a request for FDA emergency use authorization, by late January 2021.

In addition, China and Russia have released vaccines, and there are currently 61 vaccines being investigated in clinical trials and at least 85 preclinical products under active investigation.

The vaccine candidates are using both conventional and novel mechanisms of action to elicit an immune response in patients. Conventional methods include attenuated inactivated (killed) virus and recombinant viral protein vaccines to develop immunity. Novel approaches include replication-deficient, adenovirus vector-based vaccines that contain the viral protein, and mRNA-based vaccines, such as the Pfizer and Moderna vaccines, that encode for a SARS-CoV-2 spike protein.

"The special vaccine concern for immunocompromised individuals is introduction of a live virus," Stohl said. "Neither the Moderna nor Pfizer vaccines are live viruses, so there should be no special contraindication for such individuals."

Live vaccine should be avoided in immunocompromised patients, and currently, live SARS-CoV-2 vaccines are only being developed in India and Turkey.

It is not unusual for vaccine trials to begin with cohorts that exclude participants with various health conditions, including those who are immunocompromised. These groups are generally then evaluated in phase 4 trials, or postmarketing surveillance. While the precise number of immunosuppressed adults in the United States is not known, the numbers are believed to be rising because of increased life expectancy among immunosuppressed adults as a result of advances in treatment and new and wider indications for therapies that can affect the immune system.

According to data from the 2013 National Health Interview Survey, an estimated 2.7% of U.S. adults are immunosuppressed. This population covers a broad array of health conditions and medical specialties; people living with inflammatory or autoimmune conditions, such as inflammatory rheumatic diseases (rheumatoid arthritis, axial spondyloarthritis, lupus); inflammatory bowel disease (Crohn's disease and ulcerative colitis); psoriasis; multiple sclerosis; organ transplant recipients; patients undergoing chemotherapy; and life-long immunosuppression attributable to HIV infection.

As the vaccines begin to roll out and become available, how should clinicians advise their patients, in the absence of any clinical trial data?

Risk vs. Benefit

Gilaad Kaplan, MD, MPH, a gastroenterologist and professor of medicine at the University of Calgary (Alta.), noted that the inflammatory bowel disease (IBD) community has dealt with tremendous anxiety during the pandemic because many are immunocompromised because of the medications they use to treat their disease.

"For example, many patients with IBD are on biologics like anti-TNF [tumor necrosis factor] therapies, which are also used in other immune-mediated inflammatory diseases such as rheumatoid arthritis," he said. "Understandably, individuals with IBD on immunosuppressive medications are concerned about the risk of severe complications due to COVID-19."

The entire IBD community, along with the world, celebrated the announcement that multiple vaccines are protective against SARS-CoV-2, he noted. "Vaccines offer the potential to reduce the spread of COVID-19, allowing society to revert back to normalcy," Kaplan said. "Moreover, for vulnerable populations, including those who are immunocompromised, vaccines offer the potential to directly protect them from the morbidity and mortality associated with COVID-19."

That said, even though the news of vaccines are extremely promising, some cautions must be raised regarding their use in immunocompromised populations, such as persons with IBD. "The current trials, to my knowledge, did not include immunocompromised individuals and thus, we can only extrapolate from what we know from other trials of different vaccines," he explained. "We know from prior vaccines studies that the immune response following vaccination is less robust in those who are immunocompromised as compared to a healthy control population."

Kaplan also pointed to recent reports of allergic reactions that have been reported in healthy individuals. "We don't know whether side effects, like allergic reactions, may be different in unstudied populations," he said. "Thus, the medical and scientific community should prioritize clinical studies of safety and effectiveness of COVID-19 vaccines in immunocompromised populations."

So, what does this mean for an individual with an immune-mediated inflammatory disease like Crohn's disease or ulcerative colitis who is immunocompromised? Kaplan explained that it is a balance between the potential harm of being infected with COVID-19 and the uncertainty of receiving a vaccine in an understudied population. For those who are highly susceptible to dying from COVID-19, such as an older adult with IBD, or someone who faces high exposure, such as a health care worker, the potential protection of the vaccine greatly outweighs the uncertainty.

"However, for individuals who are at otherwise lower risk – for example, young and able to work from home – then waiting a few extra months for postmarketing surveillance studies in immunocompromised populations may be a reasonable approach, as long as these individuals are taking great care to avoid infection," he said.

No Waiting Needed

Joel M. Gelfand, MD, MSCE, professor of dermatology and epidemiology at the University of Pennsylvania, Philadelphia, feels that the newly approved vaccine should be safe for most of his patients.

"Patients with psoriatic disease should get the mRNA-based COVID-19 vaccine as soon as possible based on eligibility as determined by the CDC and local public health officials," he said. "It is not a live vaccine, and therefore patients on biologics or other immune-modulating or immune-suppressing treatment can receive it."

However, the impact of psoriasis treatment on immune response to the mRNA-based vaccines is not known. Gelfand noted that, extrapolating from the vaccine literature, there is some evidence that methotrexate reduces response to the influenza vaccine. "However, the clinical significance of this finding is not clear," he said. "Since the mRNA vaccine needs to be taken twice, a few weeks apart, I do not recommend interrupting or delaying treatment for psoriatic disease while undergoing vaccination for COVID-19."

Given the reports of allergic reactions, he added that it is advisable for patients with a history of life-threatening allergic reactions such as anaphylaxis or who have been advised to carry an epinephrine autoinjector, to talk with their health care provider to determine if COVID-19 vaccination is medically appropriate.

The National Psoriasis Foundation has issued guidance on COVID-19, explained Steven R. Feldman, MD, PhD, professor of dermatology, pathology, and social sciences & health policy at Wake Forest University, Winston-Salem, N.C., who is also a member of the committee that is working on those guidelines and keeping them up to date. "We are in the process of updating the guidelines with information on COVID vaccines," he said.

He agreed that there are no contraindications for psoriasis patients to receive the vaccine, regardless of whether they are on immunosuppressive treatment, even though definitive data are lacking. "Fortunately, there's a lot of good data coming out of Italy that patients with psoriasis on biologics do not appear to be at increased risk of getting COVID or of having worse outcomes from COVID," he said.

Patients are going to ask about the vaccines, and when counseling them, clinicians should discuss the available data, the residual uncertainty, and patients' concerns should be considered, Feldman explained. "There may be some concern that steroids and cyclosporine would reduce the effectiveness of vaccines, but there is no concern that any of the drugs would cause increased risk from nonlive vaccines."

He added that there is evidence that "patients on biologics who receive nonlive vaccines do develop antibody responses and are immunized."

Boosting Efficacy

Even prior to making their announcement, the American College of Rheumatology had said that they would endorse the vaccine for all patients, explained rheumatologist Brett Smith, DO, from Blount Memorial Physicians Group and East Tennessee Children's Hospital, Alcoa. "The vaccine is safe for all patients, but the problem may be that it's not as effective," he said. "But we don't know that because it hasn't been tested."

With other vaccines, biologic medicines are held for 2 weeks before and afterwards, to get the best response. "But some patients don't want to stop the medication," Smith said. "They are afraid that their symptoms will return."

As for counseling patients as to whether they should receive this vaccine, he explained that he typically doesn't try to sway patients one way or another until they are really high risk. "When I counsel, it really depends on the individual situation. And for this vaccine, we have to be open to the fact that many people have already made up their mind."

There are a lot of questions regarding the vaccine. One is the short time frame of development. "Vaccines typically take 6-10 years to come on the market, and this one is now available after a 3-month study," Smith said. "Some have already decided that it's too new for them."

The process is also new, and patients need to understand that it doesn't contain an active virus and "you can't catch coronavirus from it."

Smith also explained that, because the vaccine may be less effective in a person using biologic therapies, there is currently no information available on repeat vaccination. "These are all unanswered questions," he said. "If the antibodies wane in a short time, can we be revaccinated and in what time frame? We just don't know that yet."

Philip D. Bonomi, MD, a professor of medical oncology at Rush Medical College, Chicago, explained that one way to ensure a more optimal response to the vaccine would be to wait until the patient has finished chemotherapy. "The vaccine can be offered at that time, and in the meantime, they can take other steps to avoid infection," he said. "If they are very immunosuppressed, it isn't worth trying to give the vaccine."

Cancer patients should be encouraged to stay as healthy as possible, and to wear masks and social distance. "It's a comprehensive approach. Eat healthy, avoid alcohol and tobacco, and exercise. [These things] will help boost the immune system," Bonomi said. "Family members should be encouraged to get vaccinated, which will help them avoid infection and exposing the patient."

Jim Boonyaratanakornkit, MD, PhD, an infectious disease specialist who cares for cancer patients at the Fred Hutchinson Cancer Research Center, agreed. "Giving a vaccine right after a transplant is a futile endeavor," he said. "We need to wait 6 months to have an immune response."

He pointed out there may be a continuing higher number of cases, with high levels peaking in Washington in February and March. "Close friends and family should be vaccinated if possible," he said, "which will help interrupt transmission."

The vaccines are using new platforms that are totally different, and there is no clear data as to how long the antibodies will persist. "We know that they last for at least 4 months," said Boonyaratanakornkit. "We don't know what level of antibody will protect them from COVID-19 infection. Current studies are being conducted, but we don't have that information for anyone yet.

In mid-November, Pfizer/BioNTech were the first with surprising positive protection interim data for their coronavirus vaccine, BNT162b2. A week later, Moderna released interim efficacy results showing its coronavirus vaccine, mRNA-1273, also protected patients from developing SARS-CoV-2 infections. Both studies included mostly healthy adults. A diverse ethnic and racial vaccinated population was included. A reasonable number of persons aged over 65 years, and persons with stable compromising medical conditions were included. Adolescents aged 16 years and over were included. Younger adolescents have been vaccinated or such studies are in the planning or early implementation stage as 2020 came to a close.
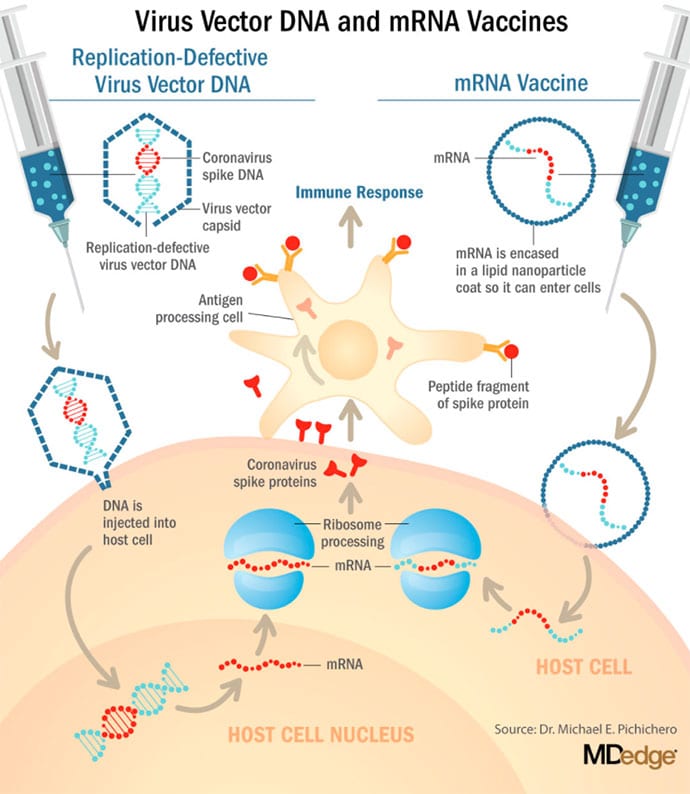
 

These are new and revolutionary vaccines, although the ability to inject mRNA into animals dates back to 1990, technological advances today make it a reality.1 Traditional vaccines typically involve injection with antigens such as purified proteins or polysaccharides or inactivated/attenuated viruses. mRNA vaccines work differently. They do not contain antigens. Instead, they contain a blueprint for the antigen in the form of genetic material, mRNA. In the case of Pfizer's and Moderna's vaccines, the mRNA provides the genetic information to synthesize the spike protein that the SARS-CoV-2 virus uses to attach to and infect human cells. Each type of vaccine is packaged in proprietary lipid nanoparticles to protect the mRNA from rapid degradation, and the nanoparticles serve as an adjuvant to attract immune cells to the site of injection. (The properties of the respective lipid nanoparticle packaging may be the factor that impacts storage requirements discussed below.) When injected into muscle (myocyte), the lipid nanoparticles containing the mRNA inside are taken into muscle cells, where the cytoplasmic ribosomes detect and decode the mRNA resulting in the production of the spike protein antigen. It should be noted that the mRNA does not enter the nucleus, where the genetic information (DNA) of a cell is located, and can't be reproduced or integrated into the DNA. The antigen is exported to the myocyte cell surface where the immune system's antigen presenting cells detect the protein, ingest it, and take it to regional lymph nodes where interactions with T cells and B cells results in antibodies, T cell–mediated immunity, and generation of immune memory T cells and B cells. A particular subset of T cells – cytotoxic or killer T cells – destroy cells that have been infected by a pathogen. The SARS-CoV-2 mRNA vaccine from Pfizer was reported to induce powerful cytotoxic T-cell responses. Results for Moderna's vaccine had not been reported at the time this column was prepared, but I anticipate the same positive results.

The revolutionary aspect of mRNA vaccines is the speed at which they can be designed and produced. This is why they lead the pack among the SARS-CoV-2 vaccine candidates and why the National Institute of Allergy and Infectious Diseases provided financial, technical, and/or clinical support. Indeed, once the amino acid sequence of a protein can be determined (a relatively easy task these days) it's straightforward to synthesize mRNA in the lab – and it can be done incredibly fast. It is reported that the mRNA code for the vaccine by Moderna was made in 2 days and production development was completed in about 2 months.2

A 2007 World Health Organization report noted that infectious diseases are emerging at "the historically unprecedented rate of one per year."3 Severe acute respiratory syndrome (SARS), Zika, Ebola, and avian and swine flu are recent examples. For most vaccines against emerging diseases, the challenge is about speed: developing and manufacturing a vaccine and getting it to persons who need it as quickly as possible. The current seasonal flu vaccine takes about 6 months to develop; it takes years for most of the traditional vaccines. That's why once the infrastructure is in place, mRNA vaccines may prove to offer a big advantage as vaccines against emerging pathogens.

Early Efficacy Results Have Been Surprising

Both vaccines were reported to produce about 95% efficacy in the final analysis. That was unexpectedly high because most vaccines for respiratory illness achieve efficacy of 60%-80%, e.g., flu vaccines. However, the efficacy rate may drop as time goes by because stimulation of short-term immunity would be in the earliest reported results.

Preventing SARS-CoV-2 cases is an important aspect of a coronavirus vaccine, but preventing severe illness is especially important considering that severe cases can result in prolonged intubation/artificial ventilation, prolonged disability and death. Pfizer/BioNTech had not released any data on the breakdown of severe cases as this column was finalized. In Moderna's clinical trial, a secondary endpoint analyzed severe cases of COVID-19 and included 30 severe cases (as defined in the study protocol) in this analysis. All 30 cases occurred in the placebo group and none in the mRNA-1273–vaccinated group. In the Pfizer/BioNTech trial there were too few cases of severe illness to calculate efficacy.

Duration of immunity and need to revaccinate after initial primary vaccination are unknowns. Study of induction of B- and T-cell memory and levels of long-term protection have not been reported thus far.

Could mRNA COVID-19 Vaccines Be Dangerous in the Long Term?

These will be the first-ever mRNA vaccines brought to market for humans. In order to receive Food and Drug Administration approval, the companies had to prove there were no immediate or short-term negative adverse effects from the vaccines. The companies reported that their independent data-monitoring committees hadn't "reported any serious safety concerns." However, fairly significant local reactions at the site of injection, fever, malaise, and fatigue occur with modest frequency following vaccinations with these products, reportedly in 10%-15% of vaccinees. Overall, the immediate reaction profile appears to be more severe than what occurs following seasonal influenza vaccination. When mass inoculations with these completely new and revolutionary vaccines begins, we will know virtually nothing about their long-term side effects. The possibility of systemic inflammatory responses that could lead to autoimmune conditions, persistence of the induced immunogen expression, development of autoreactive antibodies, and toxic effects of delivery components have been raised as theoretical concerns.4-6 None of these theoretical risks have been observed to date and postmarketing phase 4 safety monitoring studies are in place from the Centers for Disease Control and Prevention and the companies that produce the vaccines. This is a risk public health authorities are willing to take because the risk to benefit calculation strongly favors taking theoretical risks, compared with clear benefits in preventing severe illnesses and death.

What About Availability?

Pfizer/BioNTech expects to be able to produce up to 50 million vaccine doses in 2020 and up to 1.3 billion doses in 2021. Moderna expects to produce 20 million doses by the end of 2020, and 500 million to 1 billion doses in 2021. Storage requirements are inherent to the composition of the vaccines with their differing lipid nanoparticle delivery systems. Pfizer/BioNTech's BNT162b2 has to be stored and transported at –80° C, which requires specialized freezers, which most doctors' offices and pharmacies are unlikely to have on site, or dry ice containers. Once the vaccine is thawed, it can only remain in the refrigerator for 24 hours. Moderna's mRNA-1273 will be much easier to distribute. The vaccine is stable in a standard freezer at –20° C for up to 6 months, in a refrigerator for up to 30 days within that 6-month shelf life, and at room temperature for up to 12 hours.

Timelines and Testing Other Vaccines

Strong efficacy data from the two leading SARS-CoV-2 vaccines and emergency-use authorization Food and Drug Administration approval suggest the window for testing additional vaccine candidates in the United States could soon start to close. Of the more than 200 vaccines in development for SARS-CoV-2, at least 7 have a chance of gathering pivotal data before the front-runners become broadly available.

Testing diverse vaccine candidates, based on different technologies, is important for ensuring sufficient supply and could lead to products with tolerability and safety profiles that make them better suited, or more attractive, to subsets of the population. Different vaccine antigens and technologies also may yield different durations of protection, a question that will not be answered until long after the first products are on the market.

AstraZeneca enrolled about 23,000 subjects into its two phase 3 trials of AZD1222 (ChAdOx1 nCoV-19): a 40,000-subject U.S. trial and a 10,000-subject study in Brazil. AstraZeneca's AZD1222, developed with the University of Oxford (England), uses a replication defective simian adenovirus vector called ChAdOx1.AZD1222 which encodes the SARS-CoV-2 spike protein. After injection, the viral vector delivers recombinant DNA that is decoded to mRNA, followed by mRNA decoding to become a protein. A serendipitous manufacturing error for the first 3,000 doses resulted in a half dose for those subjects before the error was discovered. Full doses were given to those subjects on second injections and those subjects showed 90% efficacy. Subjects who received 2 full doses showed 62% efficacy. A vaccine cannot be licensed based on 3,000 subjects so AstraZeneca has started a new phase 3 trial involving many more subjects to receive the combination lower dose followed by the full dose.

Johnson and Johnson (J&J) started its phase 3 trial evaluating a single dose of JNJ-78436735 in September. Phase 3 data may be reported by the end of2020. In November, J&J announced it was starting a second phase 3 trial to test two doses of the candidate. J&J's JNJ-78436735 encodes the SARS-CoV-2 spike protein in an adenovirus serotype 26 (Ad26) vector, which is one of the two adenovirus vectors used in Sputnik V, the Russian vaccine reported to have 90% efficacy at an early interim analysis.

Sanofi and Novavax are both developing protein-based vaccines, a proven modality. Sanofi, in partnership with GlaxoSmithKline started a phase 1/2 clinical trial in the Fall 2020 with plans to commence a phase 3 trial in late December. Sanofi developed the protein ingredients and GlaxoSmithKline added one of their novel adjuvants. Novavax expects data from a U.K. phase 3 trial of NVX-CoV2373 in early 2021 and began a U.S. phase 3 study in late November. NVX-CoV2373 was created using Novavax' recombinant nanoparticle technology to generate antigen derived from the coronavirus spike protein and contains Novavax's patented saponin-based Matrix-M adjuvant.

Inovio Pharmaceuticals was gearing up to start a U.S. phase 2/3 trial of DNA vaccine INO-4800 by the end of 2020.

After Moderna and Pfizer-BioNTech, CureVac has the next most advanced mRNA vaccine. It was planned that a phase 2b/3 trial of CVnCoV would be conducted in Europe, Latin America, Africa, and Asia. Sanofi is also developing a mRNA vaccine as a second product in addition to its protein vaccine.

Vaxxinity planned to begin phase 3 testing of UB-612, a multitope peptide–based vaccine, in Brazil by the end of 2020.

However, emergency-use authorizations for the Pfizer and Moderna vaccines could hinder trial recruitment in at least two ways. Given the gravity of the pandemic, some stakeholders believe it would be ethical to unblind ongoing trials to give subjects the opportunity to switch to a vaccine proven to be effective. Even if unblinding doesn't occur, as the two authorized vaccines start to become widely available, volunteering for clinical trials may become less attractive.

Pichichero is a specialist in pediatric infectious diseases, and director of the Research Institute at Rochester (N.Y.) General Hospital. He said he has no relevant financial disclosures. Email Pichichero at pdnews@mdedge.com.

.

Earlier this week, Medscape spoke with Nora Disis, MD, about vaccinating cancer patients. Disis is a medical oncologist and director of both the Institute of Translational Health Sciences and the Cancer Vaccine Institute, the University of Washington, Seattle, Washington. As editor-in-chief of JAMA Oncology, she has watched COVID-19 developments in the oncology community over the past year.

Here are a few themes that Disis said oncologists should be aware of as vaccines eventually begin reaching cancer patients.

We should expect cancer patients to respond to vaccines. Historically, some believed that cancer patients would be unable to mount an immune response to vaccines. Data on other viral vaccines have shown otherwise. For example, there has been a long history of studies of flu vaccination in cancer patients, and in general, those vaccines confer protection. Likewise for pneumococcal vaccine, which, generally speaking, cancer patients should receive.

Special cases may include hematologic malignancies in which the immune system has been destroyed and profound immunosuppression occurs. Data on immunization during this immunosuppressed period are scarce, but what data are available suggest that once cancer patients are through this immunosuppressed period, they can be vaccinated successfully.

The type of vaccine will probably be important for cancer patients. Currently, there are 61 coronavirus vaccines in human clinical trials, and 17 have reached the final stages of testing. At least 85 preclinical vaccines are under active investigation in animals.

Both the Pfizer-BioNTech and Moderna COVID vaccines are mRNA type. There are many other types, including protein-based vaccines, viral vector vaccines based on adenoviruses, and inactivated or attenuated coronavirus vaccines.

The latter vaccines, particularly attenuated live virus vaccines, may not be a good choice for cancer patients. Especially in those with rapidly progressing disease or on chemotherapy, attenuated live viruses may cause a low-grade infection.

Incidentally, the technology used in the genetic, or mRNA, vaccines developed by both Pfizer-BioNTech and Moderna was initially developed for fighting cancer, and studies have shown that patients can generate immune responses to cancer-associated proteins with this type of vaccine.

These genetic vaccines could turn out to be the most effective for cancer patients, especially those with solid tumors.

Our understanding is very limited right now. Neither the Pfizer-BioNTech nor the Moderna early data discuss cancer patients. Two of the most important questions for cancer patients are dosing and booster scheduling. Potential defects in lymphocyte function among cancer patients may require unique initial dosing and booster schedules. In terms of timing, it is unclear how active therapy might affect a patient's immune response to vaccination and whether vaccines should be timed with therapy cycles.

Vaccine access may depend on whether cancer patients are viewed as a vulnerable population. Those at higher risk for severe COVID-19 clearly have a greater need for vaccination. While there are data suggesting that cancer patients are at higher risk, they are a bit murky, in part because cancer patients are a heterogeneous group. For example, there are data suggesting that lung and blood cancer patients fare worse. There is also a suggestion that, like in the general population, COVID risk in cancer patients remains driven by comorbidities.

It is likely, then, that personalized risk factors such as type of cancer therapy, site of disease, and comorbidities will shape individual choices about vaccination among cancer patients.


Scientists are now confident that a new variant of the SARS-CoV-2 virus is more contagious but say studies are underway to test its impact on containing COVID-19

What is different about this variant?

The new variant of the SARS-CoV-2 virus, known as VUI-202012/01, or lineage B.1.1.7, carries an unusually large number of mutations.

Three of the mutations have potential biological effects. These have been identified as:

  • Mutation N501Y – one of six key contact residues within the receptor-binding domain that can increase binding affinity to human and murine ACE2.

  • The spike deletion 69-70del that affects the capacity to evade human immune response

  • Mutation P681H adjacent to the furin cleavage site

How was it identified?

The variant was identified by Public Health England monitoring, following a surge in cases seen in Kent and London.

The two earliest sampled genomes belonging to B.1.1.7 lineage were collected on 20 September in Kent, followed by another on 21 September in Greater London.

How widespread is it?

According to the COVID-19 Genomics Consortium UK (COG-UK), as of 15 December, there were 1623 genomes in the B.1.1.7 lineage.

Of these 519 were sampled in Greater London, 555 in Kent, 545 in other regions of the UK including both Scotland and Wales, and four in other countries.

Is it more contagious?

Genomic data suggests a growth rate of the new virus variant 71% higher (95% confidence level: 67% - 75%) than other variants.

Although it remains too early to say with certainty that the variant is responsible for increased numbers of cases, the New and Emerging Respiratory Virus Threats Advisory Group (NERVTAG) said on 18 December that the variant had "demonstrated exponential growth during a period when national lockdown measures were in place".

The panel concluded that that VUI-202012/01 "demonstrates a substantial increase in transmissibility compared to other variants".

Is the new variant more dangerous? 

Sharon Peacock, executive director of COG-UK, told a briefing hosted by the Science Media Centre yesterday: "We have no evidence that there is an association with a worse outcome."

Prof Tom Connor, reader at the School of Biosciences, Cardiff University, said it was too early to be sure, as outcomes were determined after 28 days following diagnosis. "We're not at that point where you'd have that outcome information to do that analysis yet," he told the briefing.

Public Health England has said: "We currently have no evidence that the variant is more likely to cause severe disease or mortality – but we are continuing investigations to understand this better."

Is the UK alone in being identified with the variant?

Experts have suggested that UK science might be just better at identifying variant strains of the virus than most other countries.

According to Prof Connor, "It is probable that similar variants are popping up around the world.

"We are sequencing in the UK at a disproportionate rate to other people, which means that we have a much better system for catching this," he told the briefing.

Is there any evidence that children are spreaders now?

At a news conference this week, Boris Johnson evaded a commitment that all children would be back at school at the start of January, reflecting suggestions that school-age children might be spreading the virus.

Experts today said that there was no evidence this was the case.

However, Judith Breuer, professor of virology and co-director of the Division of Infection and Immunity at University College London said: "We know that coronavirus is spread very easily amongst children, so it wouldn't surprise me if eventually the SARS-CoV-2 virus ended up spreading amongst children."

Will the new variant be resistant to current vaccines? 

There is no current evidence that the new variant of SARS-CoV-2 will be resistant to COVID-19 vaccines.

PHE said this week that laboratory work was currently being undertaken as a priority to understand this.

Professor Ravi Gupta, professor of clinical microbiology at the University of Cambridge said that "the new variant is very unlikely to escape vaccines because vaccines elicit T-cell responses, antibody responses, and both of those responses are targeting multiple parts of the spike".

Ugur Sahin from BioNTech, whose COVID-19 vaccine was the first to be approved for emergency use worldwide, and in the UK, said he was confident the company's vaccine would remain effective against the new variant.

However, he acknowledged that more research was needed before he could confirm the efficacy.

Was this new variant unexpected?

It is not uncommon for viruses to undergo mutations; seasonal influenza mutates every year. Variants of SARS-CoV-2 have been observed in other countries, such as Spain.

Prof Tom Solomon, director of the NIHR Health Protection Research Unit in Emerging and Zoonotic Infections, at the University of Liverpool, said: "SARS-CoV-2, the virus which causes COVID-19, is evolving and mutating all the time, as do all similar viruses. Such changes are completely to be expected."

Dr Jeremy Farrar, director of the Wellcome Trust, said the latest development showed there would still be surprises from SARS-CoV-2. "We have to remain humble and be prepared to adapt and respond to new and continued challenges as we move into 2021," he said.